
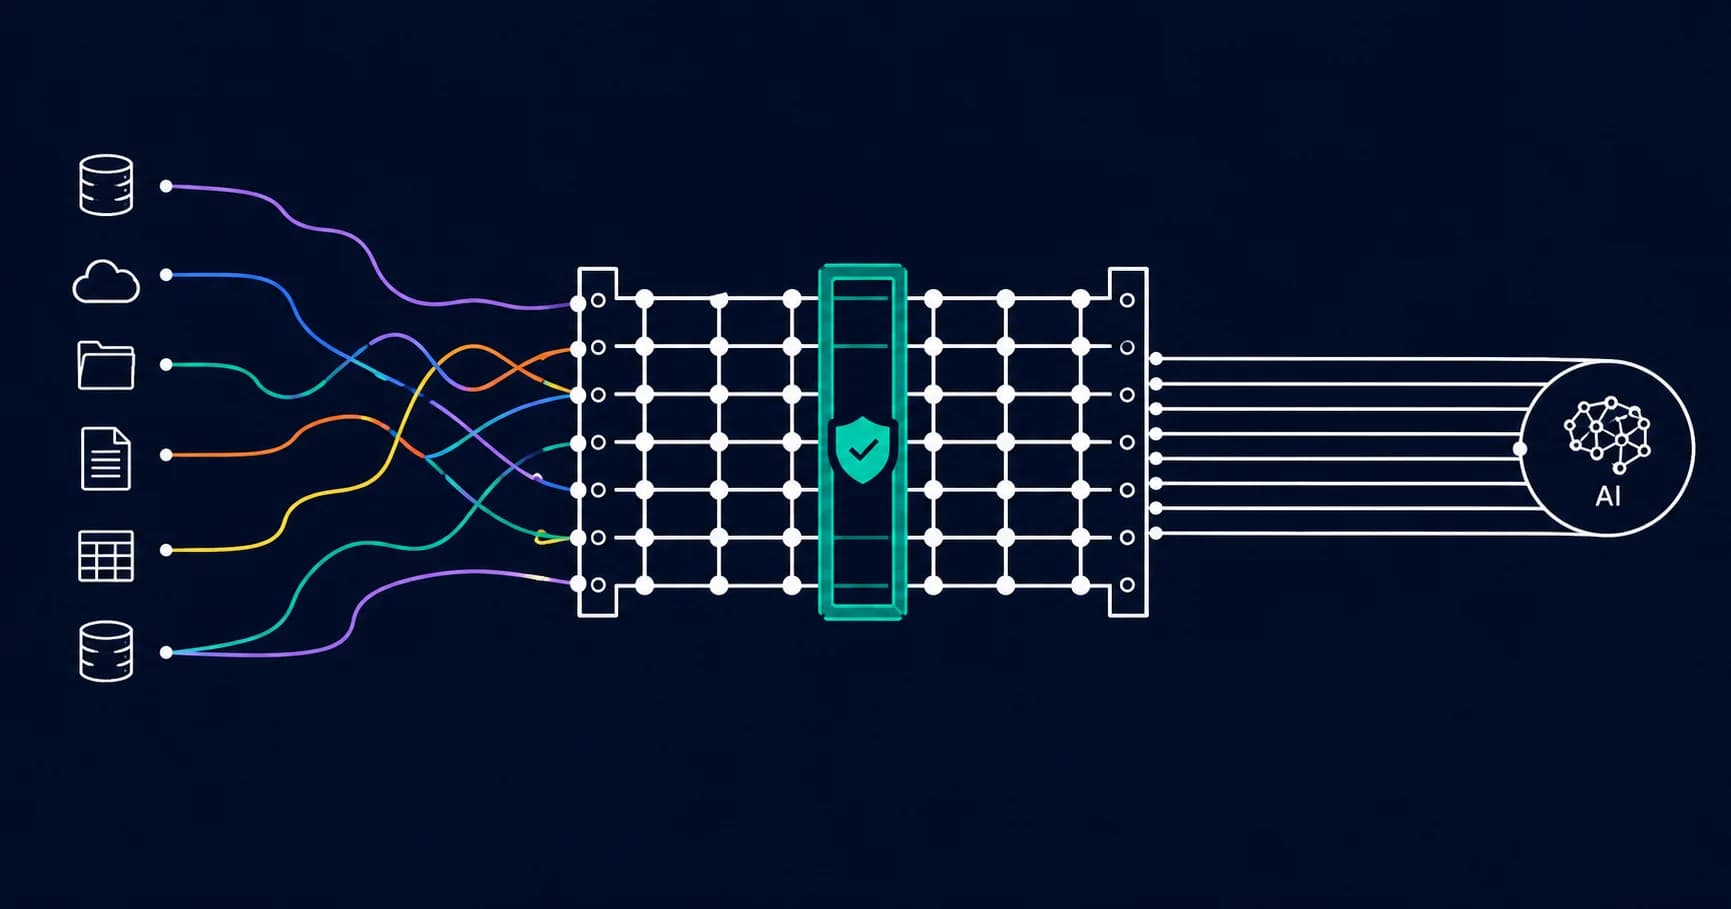
Walk into almost any clinical research organization right now and you will find the same scene. There is an AI initiative. There is a data science team. There is a proof of concept that demoed beautifully in a room full of executives. And there is a quiet, unresolved question underneath all of it: can the data actually feed this thing in production, reliably, across every study, without someone hand-stitching it together each time.
That question deserves attention alongside the choice of model. Before expanding an AI pilot, a clinical research organization needs to ask not only "which AI capability should we buy" but also "is our data operations layer ready to carry it." That is the right question. It is also the harder one.
What "data operations" actually means in a trial
Data operations is the layer between raw collection and anything useful. It is the ingestion, standardization, reconciliation, lineage, validation, and delivery of trial data into a form that a query, a report, a submission, or a model can trust. In a modern study that data arrives from electronic data capture, labs, wearables and sensors, imaging, patient-reported outcomes, and a growing list of third-party sources, each with its own format and its own idea of what a patient record looks like.
The job of the data operations layer is to make all of that reconcilable and reproducible. Not once, for one study, in one heroic sprint. Every time, across studies of different sizes and sponsors, with an audit trail that holds up under scrutiny. When people say a trial was "data limited," this layer is usually what they mean, even if they name the model or the team instead.
The data layer can become the bottleneck
Gartner’s February 2025 forecast put abandonment through 2026 at 60% for AI projects without AI-ready data. Its July 2024 survey of 1,203 data leaders found 63% lacked confidence in, or appropriate practices for, AI data management. Separately, its July 2024 forecast anticipated at least 30% abandonment after generative-AI proofs of concept by end-2025, citing data, risk, cost, and value concerns. These are forecasts and survey findings, not measured clinical-AI failure rates.
Those findings make data readiness a practical planning concern; they do not show that model quality has stopped mattering. A team should test the data path and the model together: can the inputs be reconciled, can the output meet the intended use, and can the workflow operate at its required cadence? Continuous feeds are useful for some workloads, while validated snapshots or scheduled batches are appropriate for others.
Why 2026 is different: more data, and AI everywhere in the workflow
Two forces are colliding. The first is raw volume. A 2025 TransCelerate and Tufts study announcement reported an average of 5.96 million data points for Phase III protocols in its sample of 105 Phase II and III protocols from 14 companies. That is a sample-specific benchmark, not a rule for every study. More endpoints, biomarker data, and source systems increase the work needed to reconcile a study dataset.
The second force is that AI is no longer a side project. It is being pushed into authoring, into outcome assessment, into monitoring, into the everyday work of clinical operations. When AI moves from a pilot into the production workflow, the standard it demands of the data changes. Analytics-ready data was good enough for a monthly report. AI-ready data has to be governed at the level of the individual asset, carry current version and provenance metadata, hold its lineage, and pass quality gates at the cadence the use case requires. That may be near real time, scheduled batches, or a controlled frozen dataset. That is a materially higher bar, and most environments were not built to clear it.
What a working data operations layer looks like
The organizations that get this right tend to share the same building blocks. Ingestion is automated and source-agnostic, so a new instrument or partner feed is an onboarding task rather than a rebuild. Standardization is enforced once, centrally, against common clinical data models rather than re-negotiated per study. Lineage is captured automatically, so any figure can be traced back to its source without a forensic exercise. Validation runs as a gate in the pipeline, not as a manual pass at the end. And the whole thing is reproducible across labs and studies, which is what lets a result survive being checked by someone who was not in the room when it was produced.
None of this is glamorous. It is plumbing. But it is the plumbing that decides whether an AI capability is a demo or a dependable part of the operation. Skip it and every model becomes a one-off, rebuilt by whoever happens to be on the team that quarter.
Why this hits clinical research harder than most industries
A retailer with messy data ships a slightly worse recommendation. A clinical research organization with messy data has a harder problem, because the environment is regulated and the data has to be defensible. It is not enough for a pipeline to produce the right answer. It has to be able to show its work: where each value came from, what transformed it, who validated it, and whether that chain would hold up in front of a reviewer.
That is what makes the AI governance seam so sharp in this sector. Many organizations are now running two layers at once, an enterprise automation layer built by central engineering and a citizen-developer layer built by domain teams close to the science. Both are valuable. The friction lives in the gap between them, in whether the governed pipeline and the fast local tool agree on what the data means and can both be trusted in a validated context. Closing that seam is a data operations problem before it is an AI problem.
Signs your data operations layer is not ready
A few symptoms show up again and again. Data preparation eats the team: Anaconda’s 2020 cross-industry survey found respondents spent an average of 45% of their time loading and cleaning data, a historical indicator rather than a clinical-team benchmark. Every new study feels like starting over rather than configuring a known process. Nobody can quickly answer where a specific number came from. The 2025 protocol-data study announcement also found that nearly one-third of procedures and associated data did not directly support primary or key secondary endpoints; exploratory use can still matter, so this is not a claim that the data is worthless. If several of these issues occur together, investigate the data layer as well as protocol design, model performance, and workflow ownership.
Where the business case shows up
The payoff of fixing this layer is not abstract. In one engagement, building a domain-specific AI query agent on top of a properly curated data foundation, a life sciences data team saw queries run 35% faster, with more than 250 curated fields and a tenfold increase in the data coverage available to the people asking questions. The model mattered, but the model only worked because the data beneath it was governed and reconcilable first.
The same principle shows up in data harmonization work. Unifying more than 50 national datasets into a single analytics platform, used by over 1,000 people across more than 15 countries, cut manual preparation by about 60%. The headline was the platform. The value was the operations layer underneath that made the platform trustworthy at scale. These are market access and analytics outcomes, not evidence of clinical model validity. They illustrate how a governed data layer can reduce operational effort; model evaluation remains a separate task.
How to Strengthen the Clinical AI Data Foundation
If your team is staring at a stalled AI pilot, or bracing for the data volume of the next protocol, the most useful next move is usually not another model evaluation. It is an honest look at the data operations layer: how data gets in, how it gets standardized, how it gets validated, and whether any of that is reproducible without heroics. That is the work DataDrill does, embedded alongside data and clinical teams in regulated environments, building the pipelines and governance that let AI run in production rather than in a demo.
Final Thought
The winners in clinical AI will not be the teams with the cleverest model. They will be the teams whose data was ready when the model arrived.
The supporting engineering work is described in DataDrill’s life sciences data engineering services. A related analysis explains why healthcare AI pilots fail to scale. Approved examples of the underlying data and AI work are available in the case studies. For the next layer of preparation, read how to build an agent-ready data foundation.